Antidepressants and Fertility: A Longer Wait Is Not a Stop Order
You are trying to conceive, and you take an antidepressant. Someone — a friend, a forum, occasionally a clinician in a hurry — suggested you come off it so pregnancy would come faster. Or the medication never came up at all, and you are left wondering whether the pill is why this month keeps ending the same way.
Those are different problems. Depression is an illness. An SSRI is one treatment for it. A study about the drug does not cancel the illness, and the illness does not make the drug a detail you can ignore.
Depression is not a side note
Depression changes sleep, appetite, libido, and whether a plan survives past Tuesday. It can also fill you with doubt about raising a child at all. That is the illness talking. It is not a reason to delete a prescription that is keeping you able to work, relate to people, and stay in care.
I am not your psychiatrist, and I will not rank a cycle calendar above your mood. If the medication is doing a job, fertility counseling that pretends otherwise is incomplete.
What the studies actually separate
The piece I teach from is a commentary, not a trial from this clinic. In December 2020, Kaing and Jaswa published “Rubik’s cube of depression, antidepressants, and fertility” in Fertility and Sterility. They were sorting out why large studies had disagreed — some found an effect, some did not. A lot of that disagreement is measurement. A form that says “I take something” does not record the drug, the dose, or whether you take it.
When exposure was measured more carefully than a checkbox, long-term SSRI use lined up with a lower chance of conceiving. One analysis put that reduction near a quarter for extensive use. Fluoxetine was one medication that discussion singled out. In plain language: it can take longer to get pregnant. That figure is not your personal odds, and it is not a finding that you cannot conceive.
The other half is the part I refuse to drop. In that same reading, SSRI use was not tied to a higher miscarriage rate, and it was not tied to a lower chance of a live birth once a pregnancy was underway. Arriving there may be slower. Staying pregnant was not the outcome that got worse.
Much of this evidence sits inside IVF and IUI, where other medications are already in the protocol. I do not pretend an unmedicated cycle copies that setting. A softer response to stimulation is a question for your reproductive endocrinologist. It is still not a reason for me to take you off an SSRI.
Stopping is not a fertility plan
Nothing on this page is a taper. If an antidepressant is what keeps you functional, you stay on it unless the clinician who prescribes it changes it with you — psychiatrist, obstetrician, or primary care. Stopping on your own, especially all at once, can make you ill. It can also wreck the months you were hoping to use.
I will not switch the drug, cut the dose, or label fluoxetine the one you must leave. If you want to ask whether another medication would fit a trying season, ask the person who knows your psychiatric history. Bring them the question. Do not hand it to me as if acupuncture were a replacement.
A slower start is not the whole chart
A longer wait to conceive is not proof the SSRI is the only factor in the room. Thyroid, iron, ovulation, the uterine lining, endometriosis, adenomyosis, and a partner’s semen analysis can all share the same file. If you were told there is nothing left to check, start on unexplained infertility. If a stimulation or transfer is already scheduled, that calendar lives on IVF support.
Mood care that is not this medication question — anxiety, trauma, the weight of trying — lives on depression, anxiety, and trauma. The wider door, whether or not you are trying this year, is women’s health.
The Fertility Pyramid, with the prescription in the middle
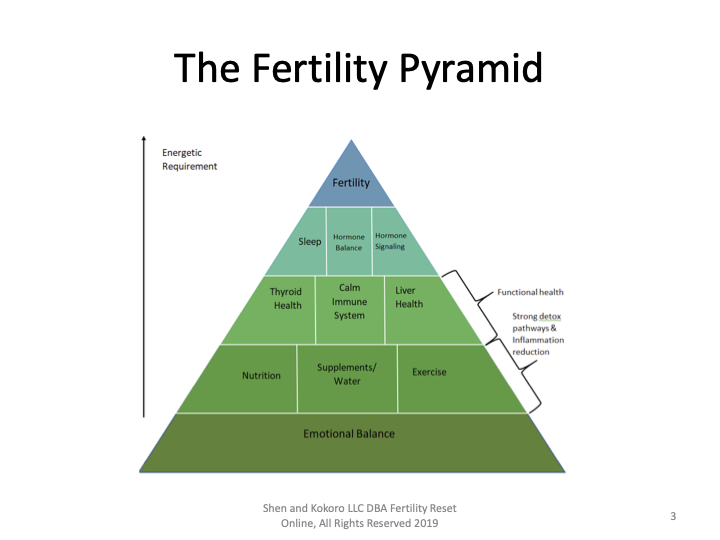
An antidepressant is not the apex of this pyramid, and it is not the ground under it either. The base is whether you can sleep, eat, and stay well enough that any plan is possible — which, for a lot of people, means depression is actually treated. The middle holds the medical picture: the prescription, the cycle, the labs already drawn, and an IVF calendar if one exists. The apex is a conception. Removing the medication to chase that apex, while depression is still running the base, tends to cost you both.
A bottle aimed at egg quality does not hold a mood that is coming apart, and a stable SSRI does not finish a workup nobody ran. Money spent at the top still has to pass through sleep, food, and a nervous system that can tolerate the wait.
The visit and the prescription are one plan, not two rivals. Sleep, and a mood that holds, are what the rest of the work stands on. Acupuncture is the piece I use for stress and recovery while you keep trying. The drug stays with your prescriber. I am not interested in a version of care that asks you to abandon one so the other can look decisive.
Months already underway
The eggs you might ovulate later this season have been maturing for months, inside the life you are already living — including a steady dose, if that is what you are on. Those months are not an excuse for a sudden stop so you can “clear the drug” before a retrieval. A body knocked off its medication is not a cleaner foundation. If you and your prescriber ever change a dose, that change needs a runway, not a decision the night a cycle starts.
When a retrieval or a transfer already has a date, we work inside those weeks. Less time means a narrower plan. It does not mean you abandon a medication that is keeping you steady.
Honest limits
I cannot tell you that your SSRI is why this is slow, or that it is innocent. I cannot promise a pregnancy, a stronger stimulation response, or that acupuncture will shorten the wait. The “near a quarter” figure is one analysis, discussed mostly in assisted reproduction. It is not a number with your name on it.
If you feel unsafe, or you are thinking of harming yourself, contact emergency services or a crisis line. Do not wait on an acupuncture visit.
What I can do is keep the lanes clear: your prescriber for the medication, a fertility workup for what was skipped, and adjunct care for the person who has to live through the wait. The clinic path — consult, records, then a plan — is on fertility programs.
Next step
Request a consult with three things in hand: the medication list, how long you have been taking it, and the name of the clinician who prescribes it. I also want to know which tests have already been done.
If you are outside Las Vegas, or you want orientation before a visit, the free email course is the Fertility Reset Roadmap. It covers prep mistakes. It does not tell you to discontinue a prescription.
Explore fertility programs, women’s health, depression, anxiety, and trauma care, IVF support, unexplained infertility, and contact.

Common questions
Should I stop my antidepressant to get pregnant?
No. Depression is an illness, and an SSRI that is keeping you functional stays in place unless the clinician who prescribes it changes it with you. A possible longer time to conception is not a taper schedule. Do not stop suddenly.
Do SSRIs raise the chance of miscarriage?
In the literature I teach from, SSRI use was not tied to a higher miscarriage rate, or to a lower chance of a live birth, once pregnancy had started. That is not a promise about your pregnancy. Obstetric decisions stay with your OB and your prescriber.
Is fluoxetine different from other SSRIs?
The commentary I use flagged fluoxetine in particular as associated with a lower chance of conceiving. That is not an instruction to switch. If you want to ask whether a different medication would fit a trying plan, ask the person who prescribes it.
Can acupuncture replace my antidepressant?
No. Acupuncture here is adjunct care for sleep, stress, and a fertility plan. It is not an antidepressant, and it is not a reason to discontinue one.
Does this only apply if I am doing IVF?
A lot of the evidence comes from IVF and IUI. It may not describe an unmedicated cycle the same way. Either way, the medication decision does not move to me, and the rest of the workup still matters.
Ready to find out what is actually going on?
Book a consult. One conversation, tell me what has been happening and what you have already tried.
Book a ConsultNot in Las Vegas? Start with my free Fertility Reset Roadmap. A 5-day email course where I walk you through the 5 most common mistakes you're probably making when trying to get pregnant
Learn about the Fertility Reset Roadmap